Key Takeaways
- Retatrutide showed A1C reductions up to 2.02 percentage points at the 12 mg dose in phase 2 trials, with 94-95% of participants reaching A1C below 7%, significantly outperforming approved drugs like dulaglutide.
- Retatrutide remains unapproved and investigational as of 2026; it is only available through clinical trials and should never be purchased from online or compounding sources due to unknown purity and lack of medical oversight.
- The drug's triple-receptor mechanism (GLP-1, GIP, and glucagon) works on multiple metabolic pathways simultaneously, likely contributing to superior A1C and weight loss results compared to single-pathway diabetes medications.
- Common gastrointestinal side effects include nausea, diarrhea, and vomiting; gradual dose escalation during trials helped reduce these effects, but long-term safety profile remains unknown.
- Patients should continue using proven, approved diabetes treatments with their primary care team rather than waiting for retatrutide approval, as early trial results do not guarantee individual outcomes.
- About 62% of trial participants receiving the 12 mg dose achieved A1C below 5.7% (normal range), though this small, short-term study finding should not be treated as a guaranteed outcome for any individual patient.
If you follow diabetes research or wellness news, you may have seen bold claims about a new injectable drug and its effect on blood sugar. Retatrutide a1c reduction results from early clinical trials have caught the attention of patients, doctors, and health-focused communities across Tampa and Riverview. But what does the research actually show, and what does it mean for someone managing type 2 diabetes today? This guide breaks down the facts in plain language, so you can separate real science from hype.
Retatrutide is still an investigational drug. It is not yet approved by regulators for treating diabetes or any other condition. That means it is not something your primary care doctor can prescribe right now. Still, the early data is worth understanding, especially if you or someone you love is working to manage blood sugar. This article walks through what retatrutide is, what the trials found, and how it fits into the bigger picture of diabetes care available through primary care today.
What Is Retatrutide and How Does It Work?
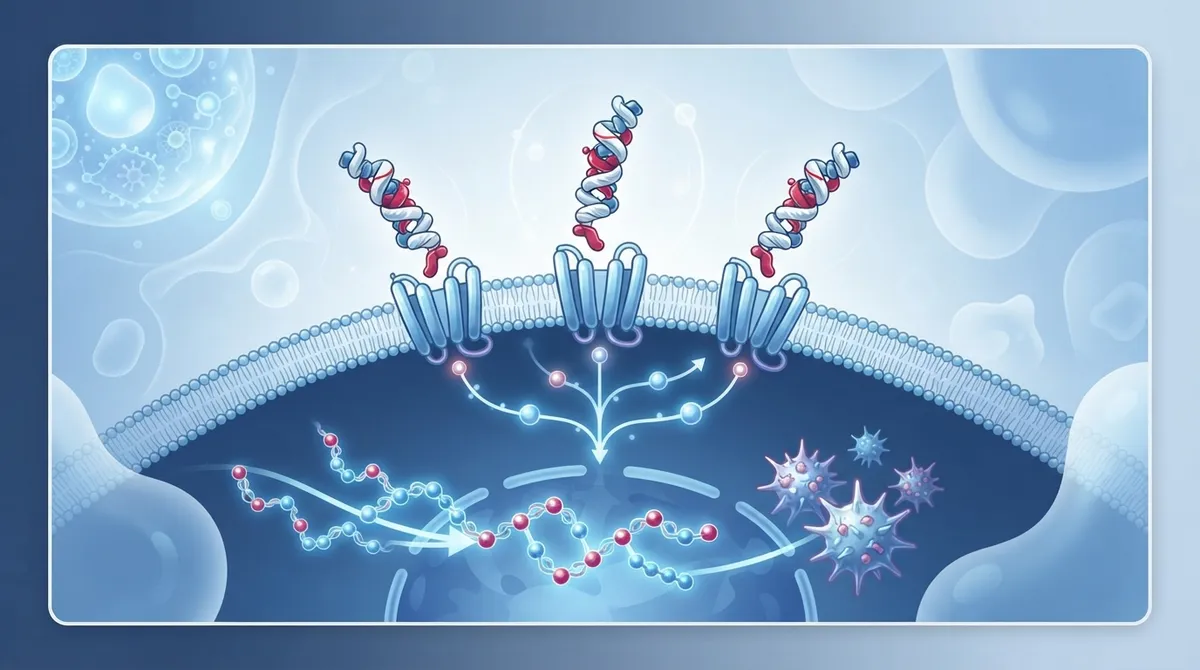
Retatrutide is a once-weekly injectable drug still being tested in clinical trials. It is designed to activate three different receptors in the body at once: GLP-1, GIP, and glucagon. This is different from many older diabetes drugs that target only one pathway.
Researchers believe this triple-action approach may explain why retatrutide has shown strong results for both blood sugar control and weight loss in early studies. It is being studied for type 2 diabetes, obesity, and other metabolic conditions. However, being studied is not the same as being approved. No regulatory body has cleared retatrutide for routine use in patients as of late 2026.
Why Triple-Hormone Activity Matters
Each of the three receptors that retatrutide targets plays a different role in metabolism:
- GLP-1 helps control appetite and slows digestion, which can lower blood sugar spikes after meals
- GIP supports insulin release and may improve how the body uses fat for energy
- Glucagon receptor activity may boost calorie burning and support weight loss
By working on all three pathways together, researchers hope retatrutide can offer stronger results than drugs that only target one receptor. This is the theory behind why early A1C reduction numbers have been so notable.
What the Clinical Trial Data Actually Shows
The most detailed data on retatrutide a1c reduction comes from a phase 2 trial published in The Lancet in 2023. This study followed adults with type 2 diabetes for 36 weeks. Participants had a starting average A1C of about 8.3%, which is considered poorly controlled diabetes.
The trial compared different doses of retatrutide against both a placebo and dulaglutide, an already-approved diabetes medication. The results were dose-dependent, meaning higher doses led to bigger reductions in A1C.
Key Results by Dose
|
Dose |
Average A1C Reduction (36 weeks) |
Percent Reaching A1C Below 7% |
|---|---|---|
|
0.5 mg |
0.43 percentage points |
26% |
|
4 mg |
1.30% to 1.39% |
72% |
|
8 mg |
1.88% to 1.99% |
94% |
|
12 mg |
2.02% |
95% |
|
Placebo |
0.01% |
13% |
For comparison, participants who received dulaglutide 1.5 mg, a widely used approved diabetes drug, saw an average A1C reduction of about 1.41 percentage points. The 12 mg dose of retatrutide outperformed this comparator in the trial, while the 4 mg dose produced results roughly similar to dulaglutide.
One especially notable finding: about 62% of people receiving the 12 mg dose reached an A1C below 5.7%, which is considered a normal, non-diabetic range. In the placebo group, essentially no one reached this level. That said, this was a small, short-term study, and these numbers should not be treated as a guarantee for any individual patient.
What About Phase 3 Data?
In March 2026, Eli Lilly reported early results from a phase 3 trial called TRANSCEND-T2D-1. According to the company, average A1C reductions ranged from about 1.7% to 2.0% across different doses at 40 weeks, compared to about 0.8% with placebo. These numbers are promising, but they come from a company announcement rather than a fully published, independently reviewed study. Patients and clinicians should wait for complete data and regulatory review before drawing firm conclusions.
Does Retatrutide Lower A1C Independently of Weight Loss?
This is one of the most common questions patients ask. Retatrutide is well known for producing significant weight loss in trial participants, so it is natural to wonder if the A1C improvements are simply a side effect of shedding pounds.
The honest answer is that both effects likely work together. Weight loss does improve insulin sensitivity and blood sugar control on its own. But the triple-hormone action of retatrutide may also directly affect insulin release and glucose metabolism, separate from weight changes. Untangling exactly how much credit belongs to each mechanism will require more research over time.
How Does Retatrutide Compare to Other GLP-1 Medications?
Patients considering diabetes treatment options often want to know how new drugs stack up against ones already on the market. Here is a general comparison based on available trial data:
- Dulaglutide (approved): Reduced A1C by about 1.41 percentage points in the same phase 2 trial that studied retatrutide
- Semaglutide (approved): Has shown A1C reductions in the range of 1.5% to 1.8% in its own separate trials, depending on dose
- Tirzepatide (approved): A dual-receptor drug that has demonstrated strong A1C and weight loss results in its own trials
- Retatrutide (investigational): Showed A1C reductions up to about 2.0 percentage points at higher doses in early trials, though it remains unapproved
It is worth noting that these are not head-to-head comparisons across identical trial conditions, except where retatrutide was directly compared to dulaglutide. Differences in study populations, duration, and design make direct comparisons tricky. Patients interested in learning more about currently approved options can read about how GLP-1 medications work or explore details on semaglutide therapy available through primary care today.
Is Retatrutide FDA Approved for Diabetes or Weight Loss?
No. As of September 2026, retatrutide has not received FDA approval for type 2 diabetes, obesity, or any other condition. It remains classified as an investigational drug, meaning it is only available through controlled clinical trial settings.
This distinction matters a great deal. Some online sellers may claim to offer retatrutide for personal use, often through compounding pharmacies or unverified sources. Purchasing or using retatrutide outside of a supervised clinical trial carries real risks, including unknown purity, incorrect dosing, and lack of medical oversight. Reputable healthcare providers will not prescribe or market retatrutide as an approved treatment because doing so would be inconsistent with current regulatory standards.
Safety Considerations and Side Effects
Like other GLP-1 and multi-receptor drugs, retatrutide has shown a pattern of gastrointestinal side effects in trials. The most commonly reported issues include:
- Nausea
- Diarrhea
- Vomiting
- Reduced appetite
Researchers used gradual dose escalation during trials to help reduce these side effects. This approach, sometimes called titration, allows the body to adjust slowly to the medication rather than starting at a high dose right away.
Clinicians also need to watch for other potential risks, including:
- Dehydration from prolonged vomiting or diarrhea
- Gallbladder problems, which have been linked to rapid weight loss and similar drug classes
- Hypoglycemia, especially when combined with insulin or drugs that stimulate insulin release
Because retatrutide is still investigational, its full long-term safety profile is not yet established. Anyone considering participation in a clinical trial should discuss these risks thoroughly with a qualified physician.
Who Might Be a Candidate If Retatrutide Becomes Approved?
While it is too early to say who should receive retatrutide once and if it gains approval, the phase 2 trial gives some clues about the population studied. Participants generally had:
- Type 2 diabetes with A1C levels between 7.0% and 10.5%
- No pregnancy or breastfeeding status
- No advanced complications that were excluded from the study
This means the results may not apply to people with type 1 diabetes, mild prediabetes, or significant other health conditions. If retatrutide eventually receives approval, primary care physicians will need to carefully evaluate each patient's health history before considering it as a treatment option, much like they do today with approved medications.
How Should Patients Approach Diabetes Care Right Now?
Given that retatrutide remains unavailable outside of trials, the best path forward for most patients is working closely with a trusted primary care team using proven, approved treatments. At InCare, patients in Tampa and Riverview have access to comprehensive primary care services that include diabetes management, lab monitoring, and personalized treatment planning.
Here are steps patients can take today to manage blood sugar effectively:
- Schedule regular A1C testing to track progress over time
- Discuss approved GLP-1 or dual-agonist medications with your doctor if appropriate
- Combine medication with diet changes and physical activity for the best results
- Monitor for side effects and report them promptly to your care team
- Consider additional wellness tools like body composition analysis or metabolic breath analysis to better understand your metabolism
InCare's approach combines advanced diagnostic technology with hands-on medical guidance, helping patients make informed choices about diabetes and weight management without relying on unproven or unapproved treatments.
Common Mistakes to Avoid
As interest in retatrutide grows, it is easy to fall into a few traps. Watch out for these common mistakes:
- Buying retatrutide from online sellers or compounding sources without medical supervision
- Assuming trial results guarantee the same outcome for every individual
- Ignoring gastrointestinal side effects instead of reporting them to a doctor
- Delaying proven, approved diabetes treatment while waiting for retatrutide to become available
- Combining unapproved medications with insulin or other diabetes drugs without professional guidance
Working with a licensed clinician remains the safest way to manage diabetes, whether or not new drugs like retatrutide eventually reach the market. If you want to explore how weight management can support blood sugar goals, InCare's weight loss programs offer physician-supervised options grounded in current evidence.
Looking Ahead: What to Watch For
Retatrutide's future depends on completing phase 3 trials, publishing full data for independent review, and gaining regulatory approval. This process can take years. Patients should stay informed through reliable sources rather than social media claims or unverified marketing.
In the meantime, primary care remains the best place to manage diabetes safely. Physicians like those at Naveen Paddu, MD and Pramjeet Ahluwalia, MD can help patients understand their options, monitor progress, and adjust care plans as new treatments become available. You can also follow health updates from InCare on Facebook, Instagram, and TikTok for the latest wellness insights.
Conclusion
The research behind retatrutide a1c reduction is genuinely exciting, with some trial participants seeing A1C drops of 2 percentage points or more. But excitement should not outpace caution. Retatrutide remains an investigational drug, not an approved treatment, and patients should not seek it outside of supervised clinical trials.
For now, the smartest move is partnering with a primary care team that understands both the promise and the limits of emerging diabetes research. Whether you are managing existing diabetes, working on prediabetes, or simply want a thorough wellness checkup, our team in Tampa and Riverview is ready to help. Reach out to our care team today or book your appointment now to start building a personalized, evidence-based plan for your health. You can also visit us on Google to see what our InCare patients are saying about their experience with our Tampa and Riverview clinics.
FAQs
Q: How much can retatrutide lower A1C?
A: In phase 2 trials, retatrutide reduced A1C by up to 2.02 percentage points at the highest 12 mg dose over 36 weeks. Lower doses produced smaller reductions, ranging from about 0.43 to 1.99 percentage points depending on dose.
Q: Is retatrutide FDA approved for diabetes or weight loss?
A: No, retatrutide is not FDA approved as of 2026. It remains an investigational drug available only through clinical trials, and it should not be obtained from unverified online sources.
Q: How does retatrutide compare to semaglutide or tirzepatide for A1C reduction?
A: Retatrutide showed slightly higher A1C reductions than dulaglutide in a direct trial comparison, with results comparable to or exceeding other approved GLP-1 therapies. However, these are separate studies, so direct comparisons should be interpreted cautiously.
Q: Can retatrutide reverse prediabetes or bring A1C into the normal range?
A: In one phase 2 trial, about 62% of participants on the 12 mg dose reached an A1C below 5.7%, a level considered normal. This is a promising but early finding from a small, short-term study, not a guaranteed outcome.
Q: What side effects are linked to retatrutide?
A: The most common side effects reported in trials were nausea, diarrhea, and vomiting. Clinicians also monitor for dehydration, gallbladder issues, and hypoglycemia risk, especially when combined with insulin or other diabetes medications.